Not medical advice — this article is for general education. If you have severe symptoms or your condition is getting worse, see a doctor.
If your “sinus infection” has been going on for two months, it’s not just a stubborn cold anymore — it’s a different condition, with a different diagnostic label and often a different cause. Most people use “sinusitis” as one catch-all term, but doctors split it into acute, subacute, chronic, and recurrent categories based almost entirely on how long symptoms actually last. That distinction matters because it changes what’s likely causing it and whether home remedies and antibiotics can even fix it.
This article is part of our complete guide to sinus infections and congestion relief. It pairs with our pieces on telling viral from bacterial infections and saline irrigation — both useful for acute infections, but neither one fixes the kind of long-running or structural problem this article covers.
The real duration thresholds
Sinusitis is classified by how long symptoms have been present, not by how bad they feel:
- Acute: symptoms lasting fewer than 4 weeks. This is what most people mean by a “sinus infection” — usually viral, and it typically resolves within 7-10 days on its own.
- Subacute: symptoms lasting 4 to 12 weeks — a low-grade continuum of an infection that never fully cleared. Research specifically on this window is limited, but it’s treated clinically as a transition zone rather than its own distinct disease.
- Chronic: symptoms lasting more than 12 weeks.
- Recurrent acute: a different pattern entirely — 4 or more separate episodes of acute sinusitis in a year, each lasting at least 10 days, with symptoms actually resolving in between episodes (as opposed to chronic sinusitis, which never fully goes away).
The practical takeaway: if you’re on week 2 of a sinus infection, you’re still squarely in “give it time and manage symptoms” territory. If you’re on week 14, or this is your fourth distinct episode this year, you’re dealing with a different problem than the one home remedies and short antibiotic courses are designed to treat.
How chronic sinusitis is actually diagnosed
Crossing the 12-week mark isn’t, by itself, enough for a chronic sinusitis diagnosis. The American Academy of Otolaryngology-Head and Neck Surgery (AAO-HNS) clinical criteria require both of the following:
- At least 2 of these 4 symptoms, present for 12 weeks or more: nasal discharge (from the front or draining down the back of the throat), nasal obstruction/congestion, facial pain or pressure, and reduced or lost sense of smell.
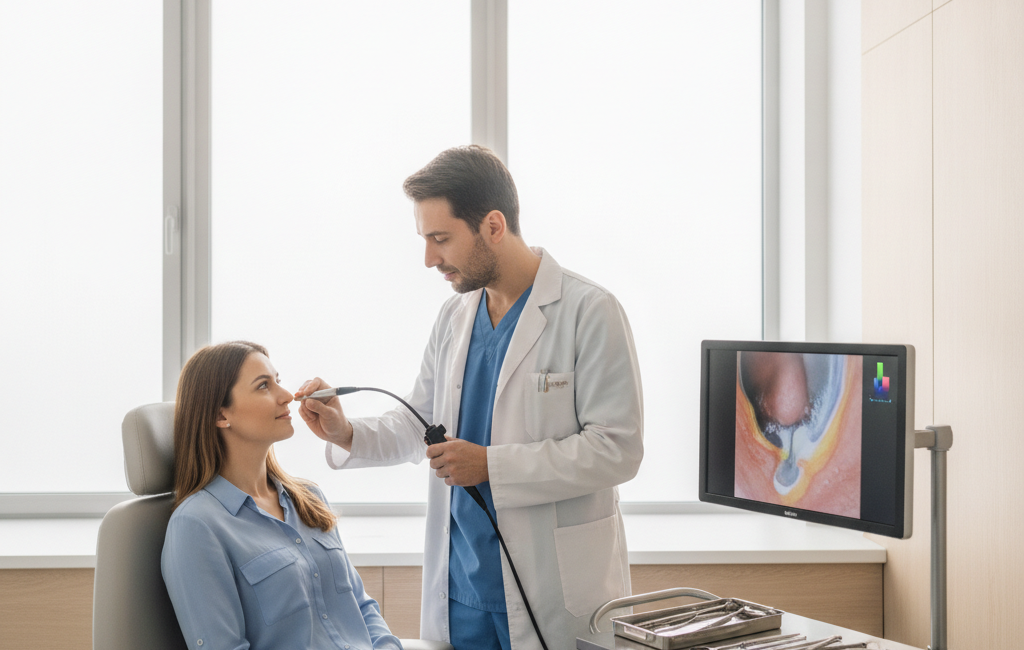
- Objective evidence of inflammation — meaning a doctor actually needs to see it, typically via nasal endoscopy (a thin camera) or CT imaging, not just take your word for the symptoms.
That second requirement is the important one for this article: chronic sinusitis, by definition, cannot be self-diagnosed from symptoms alone. It requires a clinical exam. That’s a structural reason — not just a “see a doctor to be safe” reason — why this category of sinus trouble needs an ENT (ear, nose, and throat specialist, also called an otolaryngologist) rather than another round of decongestants.
Structural causes an ENT can find that home care never will
Part of why chronic and recurrent sinusitis often don’t respond to the same measures that clear up a normal cold is that they’re frequently driven by a physical blockage rather than an active, self-limiting infection. Two of the most common structural causes:
- Nasal polyps: soft, non-cancerous growths inside the nasal passages or sinuses. They can block normal mucus drainage and airflow, creating conditions where inflammation and infection keep recurring even after each individual flare-up is treated.
- Deviated septum: when the wall between the nostrils is significantly off-center, it can narrow one side of the nasal passage and obstruct sinus drainage. Research has specifically identified a deviated septum as a risk factor for developing chronic rhinosinusitis, not just an incidental anatomical variant.
Neither of these shows up on a symptom checklist, and neither one improves with saline rinses, antibiotics, or waiting it out — they’re mechanical problems. An ENT identifies them with nasal endoscopy and/or CT imaging, and treatment ranges from medication (like nasal steroids for polyps) to surgery in more significant cases. This is the core reason recurrent or long-lasting sinus symptoms deserve a specialist visit instead of another cycle of over-the-counter treatment: no amount of home care resolves a physical obstruction.
When to actually book that ENT visit
Based on current clinical guidance, it’s worth seeing an ENT if:
- Symptoms have lasted 12 weeks or longer (meeting the chronic sinusitis pattern above).
- You’ve had 4 or more separate acute sinus infections within a year (recurrent acute sinusitis).
- An infection isn’t responding to appropriate treatment, or keeps coming back in the same pattern every time you finish a course of antibiotics.
In these situations, guidance also recommends being evaluated for underlying allergies or immune issues alongside the ENT referral, since both can drive the kind of recurring inflammation that makes sinusitis keep coming back.
Red flags that mean urgent care, not a scheduled appointment
Separately from the duration-based categories above, certain symptoms signal a possible complication where infection has spread beyond the sinuses — these need same-day medical attention, not a routine ENT booking:
- Swelling, redness, or pain around one or both eyes
- Vision changes or double vision
- Bulging of one eye (proptosis)
- Severe or rapidly worsening headache, especially with high fever
- Confusion or a stiff neck
Eye pain in particular is considered one of the most sensitive early signs of a spreading orbital infection. None of these are “wait and see if it’s chronic” symptoms — they override every other guideline in this article.
Frequently Asked Questions
Is subacute sinusitis its own condition, or just “acute sinusitis that’s taking a while”?
It’s treated more as a transition zone than a distinct disease. Clinically, it’s defined as symptoms in the 4-to-12-week range, but there’s very limited research specifically on this window compared to acute and chronic sinusitis.
Can chronic sinusitis go away without seeing a doctor?
It’s unlikely, by definition. Chronic sinusitis requires 12+ weeks of ongoing symptoms with visible inflammation on exam — if it were going to resolve on its own the way a cold does, it typically wouldn’t have reached that diagnostic threshold in the first place.
Does everyone with a deviated septum need surgery?
No. Many people have a deviated septum with no symptoms at all. It becomes a treatment consideration specifically when it’s obstructing sinus drainage and contributing to recurring or chronic sinusitis, which an ENT determines through examination and imaging.
What’s the difference between recurrent acute sinusitis and chronic sinusitis?
Recurrent acute sinusitis means separate episodes — each one resolves before the next one starts, but you get 4 or more per year. Chronic sinusitis means the inflammation never actually clears for 12+ weeks straight. They can share underlying causes (like nasal polyps or a deviated septum), but they’re diagnosed differently.
Will a CT scan or endoscopy hurt?
Nasal endoscopy uses a thin, flexible camera and is typically done in-office with local anesthetic spray, causing mild discomfort at most for most patients. A sinus CT scan is non-invasive and painless, similar to any other CT imaging.
Sources: Cleveland Clinic (Acute Sinusitis; Chronic Sinusitis); AAO-HNS Adult Sinusitis Clinical Practice Guideline diagnostic criteria for chronic rhinosinusitis; StatPearls (NCBI), “Recurrent Acute Rhinosinusitis”; peer-reviewed research on deviated septum as a risk factor for chronic rhinosinusitis (PMC9650940).



